Saturday, 13 May 2017

Posh food

I don't understand posh food. There, I've said it.

First off, there's the dishes themselves. Picture your typical fine dining menu:
  • Quenelles of axminister on a belushi rosti
  • Hipster cop three ways with charred lurex, served with a eurovision broth
  • Braised largesse with persil ravioli and germolene purée
  • Camshaft torte served with a crushing sense of ennui
 Well OK, not quite like that, but you get the idea. Why can't they just say "beef and carrots"? And why are there so rarely potatoes (or rice, or pasta)? Surely a meal needs its carbs?


And the portions  are always so small. This is the three-course meal cooked by the winner of this year's Mastechef, Saliha Mahmood-Ahmed. Sorry Saliha, I'm sure it's delicious, but I'd be stopping for chips on the way home.

So, posh food. That's why I just don't get you. My offer to accompany anyone who would like to take me to Berares, however, still stands..

Thursday, 8 December 2016

Words have power

The Last Leg, that fabulous show, announced its guest for this week's edition a couple of days back - and it's reignited an old controversy.

That guest is Ricky Gervais, and many people are concerned that a programme which got its start during the London Paralympics, and is still very disability-focused, should have as guest the man who notoriously called people "mongs", and who made Derek, a series about a man with learning difficulties, which again was widely felt to be insensitive and offensive.

Those of us who have expressed our concerns to The Last Leg's Twitter account have had many replies from Ricky Gervais fans, who don't share our concerns (to put it mildly). I've sent several of them the link to a previous post here about it, because of the space limitations on Twitter. This post is about something slightly different, though.


When someone is asked not to use certain words as insults (retard, mong, spastic, crazy... etc etc), a frequent response is, "But I wasn't talking about real disabled people!" Thing is, that's not good enough. And here's why.

If you call your slightly socially awkward friend "autistic", or describe yourself self-deprecatingly as "OCD" because you like your house to be tidy, what you're saying is being like that is a bad thing. That people with those conditions are "less than". So I'm sorry dude, but you were talking about real disabled people.

Words have power. They can empower, or they can diminish. If someone with a disability (or from another oppressed group) asks you not to use a certain word because it's offensive, is it really that much trouble to think of an alternative? It's not being PC - it's having decent manners. That's all there is to it.

Saturday, 16 August 2014

Fatigue #spoonie

How to describe this fatigue?

I'll try. Without hyperbole, and as honestly as I can. These are some of the things I think and feel.


Every limb is made of solid concrete. Moving it even the smallest amount needs all my resources.

When I walk, it is through deep, cloying mud, that pulls me back and down. If I don't get out of the marsh soon, I will drown.

Sometimes I hold the sides of my head. The muscles of my neck are too tired to hold my head upright.

I lean against the sofa back and relax the muscles that have been working so hard to maintain my posture. I'm melting into the cushions. I could never move again, even if I wanted to.

I fall asleep when I want to stay awake, and stay awake when I want to sleep.

My dreams are of waking up feeling rested, just once.

My brain is stuffed with cotton wool, but not bright and white and fluffy. It's old, and grey, and congested. The spaces are half full with oily fluid that moves unpredictably, confusing my thoughts and blanking my memory.

I'm safe here, on my sofa. If the house went on fire, I would stay here. I don't have the energy to move. I'm safe here. And so tired.

Thursday, 31 July 2014

Friday, 16 May 2014

Obstructive sleep apnoea and heart problems: the missing link?

A friend of mine died a couple of years back, of heart failure. Heart problems are very common, anid have many possible causes. He also had a condition called obstructive sleep apnoea, which has long been linked with heart problems. But nobody's ever quite known why.

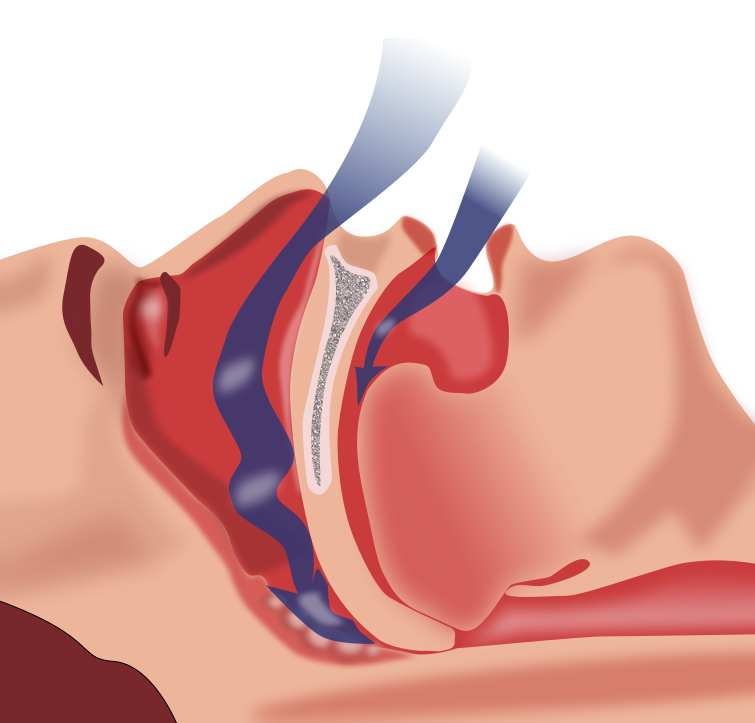
Obstructive sleep apnoea, or OSA, is surprisingly common, affecting almost a quarter of men and almost one in ten women. The muscles and soft tissues of the throat relax and collapse, blocking the airway wholly or partially and therefore interrupting breathing.


Now, for sleep to serve its purpose, we have to spend a certain amount of time in a state of deep sleep. Each time you have an episode of OSA, you enter lighter sleep or even wake very briefly in order to restore normal breathing. This cycle can repeat many times a night, up to once a minute in extreme cases.

These repeated sleep interruptions lead to the person with OSA feeling very tired during the day. They have no memory of the periods of breathlessness, so are often unaware that they are not sleeping properly.

Among the complications of OSA are heart problems: increased heart rate and blood pressure, and heart attack. The mechanism by which this happens has never been understood. Now a group of researchers at George Washington University in Washington DC seem to have uncovered it.

Our resting heart rate is maintained at an appropriately low level by a group of parasympathetic neurons in the brainstem. By mimicking OSA in rats, the researchers discovered that during OSA episodes the activity of these neurons is inhibited, leading to an increase in heart rate and the possibility of irregular heartbeat and high blood pressure.

It's too late for my friend David. But now researchers know where to focus their future work. They must try to restore the normal cardio-protective function of these neurons in people with OSA, to reduce the risk of cardiac problems, so that OSA no longer carries the risk of death.

Thursday, 1 May 2014

Writing semi-autobiographical fiction about disability #BADD14

This is my post for Blogging Against Disablism Day 2014.

Well. I've finally taken the leap of faith, and started writing the novel that's been tunneling out of my subconscious for the last couple of years. And they do say write about what you know. So I'm writing in the first person about a woman who develops MS.


But is writing semi-autobiographical fiction really worthwhile? And can a novel about disability be interesting to a general audience?

If my story was purely autobiographical, it would be a thinly disguised version of my own life story, with names and locations disguised. Firstly, this would certainly be excruciatingly boring for the reader. Secondly, parts of it would probably be actionable!

So what I'm doing instead is using my personal knowledge of my condition - multiple sclerosis - and how it affects me, and inventing a background, relationships, and story for my protagonist. I have access to the emotions I felt when I developed and was diagnosed with MS, and anecdotes from friends with MS of how their family, friends, and work colleagues reacted.

A novel is not just about the one central plotline, or it would be very short indeed. I can use my experience, both of disability and everyday life, as inspiration for plot points and to help me understand my characters' emotions. So, for instance, a real-life neighbour who takes her ferret for a walk every day in an animal carrier will be making an appearance, along with her pet.


Real life isn't connected. Random things happen at random times. Wild coincidences take us by surprise, that we wouldn't believe for a second in fiction. In a novel, however much it draws on your own life, you have to order and arrange your material to make some sort of coherent narrative .

In the end, as Tom Clancy said:

The difference between fiction and reality is that fiction has to make sense.
Do novels about disability have to be serious? Not in the least. You can see humour in any situation. My heroine is a strong, funny woman. Yes, being diagnosed with MS is a major, serious life event. But looking back on it, the process is full of humorous moments. If I can see that, so can she. Real life isn't always funny at the time. But a book can be.

And who knows? Perhaps if I can make it funny and accessible (and anyone wants to read it anyway!) it'll get over a bit of information about disability in general and MS in particular along the way. Which would be no bad thing, right? The more people know, the less stigma and disablism we'll hopefully all encounter.

So. If there's anything you think from your own experience I should try to include, please let me know in the comments. Otherwise, I'll keep you updated as much as I can. And rest assured, once it's finished I'll pimp it to death!

Tuesday, 25 February 2014

Connor Sparrowhawk: Death by Indifference


Connor Sparrowhawk was 18 years old. He was loving and much loved. He had learning difficulties, autism and epilepsy.


And he died in the bath at Slade House, an NHS assessment and treatment centre, because he was left unsupervised.

The report from a CQC inspection carried out three months after Connor's death failed the unit on a number of standards, including patient safety. Now the independent report into his death has confirmed that his death was completely preventable.

The NHS Trust concerned have listed actions they will take as a result. There's no question that giving staff training about epilepsy, auditing care plans, and so on are good things to do. But why has it taken the death of a young man to prompt what would seem to be the obvious? This was a specialist unit for people with learning disabilities, and half of those with learning disabilities also have epilepsy.

And the report shows so much passing of bucks and refusal to accept responsibility, it's unbelievable. No risk assessment of Connor's bathing arrangements. No review of his epilepsy when he entered the unit, or after it was suspected he'd had a seizure. Not all relevant staff were trained in life support. No record of the agreed observation actually happening while Connor was bathing.

Nothing will replace Connor. But it's to be hoped, at least, that this damning report will stop another family being blighted in the same way.

There's only one way to end this post, and that's by showing you Connor - Laughing Boy - as he grew up. Happy. Alive.

#justiceforLB


Friday, 21 February 2014

Multiple sclerosis and depression

We all feel down sometimes. That's natural, and part of life's rich tapestry.

But sometimes, for some of us, that short-term feeling turns into something much longer-lasting and more profound. Clinical depression can involve feelings of sadness and hopelessness, irritability, losing interest in activities, loss of ability to concentrate of make decisions, tearfulness, tiredness, sleep disturbances, and physical aches and pains. It is often linked with anxiety.


Each year, around 6% of the UK population have an episode of depression, and more than 15% will have an episode during their lifestime.Having a long-term physical illness increases your risk of depression up to about one in three, and NICE have recently issued guidelines for this situation.


Multiple sclerosis, being a long-term condition, follows this pattern. Up to 50% of people with MS experience depression at some point in their lives, and around 20% within each year. People with MS are at 7.5 times the risk of suicide of the general population.. There are several reasons for this:

  • To have MS is to be in a state of uncertainty. Your life has changed completely. You have a long-term condition with a variable course, which could potentially progress to severe disability. Your self-image changes: you fear losing independence, you may lose your job or friendships.
  • Depression can also be caused by MS's physical changes to the brain. If it damages the parts of the brain that control mood and emotional expression, behavioural changes can result, including depression.
  • MS can also affect the immune and neuroendocrine systems. For instance, studies have found changes in immune markers in people with MS who are depressed.
  • Depression can be a side-effect of certain drugs, such as the corticosteroids often prescribed for MS relapses.
There is some evidence that depression is (not surprisingly) more common around the time of a relapse, but people with more severe physical disability are not more likely to be depressed. Nor is it related to how long you've had MS.


There is no shame in having depression. It's a disabling condition just as much as a broken leg, heart disease - or, indeed, MS. It's important that we learn to recognise its onset in ourselves, and seek help. It doesn't mean weakness or need to be hidden. I see my depression as a long-term condition to be managed, like my MS.

Treatments for depression can be very effective. If you think you may be depressed, please visit your doctor and explain how you feel. If you are suicidal, contact the Samaritans.

So, if you have MS, it's entirely possible that you also have depression. Clearly not an ideal situation, but entirely treatable and manageable. As I said: all part of life's rich tapestry!

Tuesday, 13 August 2013

Twitter and Christian Jessen

You know that Doctor Christian? Yes, him off of Embarrassing Bodies and Supersize Vs Super Skinny? Well he's been getting a lot of grief recently, on Twitter and in blogs.


Not really anything new. Christian is not known for his appeasement tactics on Twitter. I think he enjoys a good ruck, to be honest. So why have I been moved to blog about him now?

I've been getting annoyed by those of his detractors who claim that Christian is misogynistic. There seem to be two main arguments going on at the moment:
  1. Breastfeeding. We all agree that breast is best. If possible. I have never seen Christian say anything different. Yet somehow, his public acknowledgement of the fact that not all women can breastfeed - which may be very reassuring to new mothers struggling with feeding - is taken as meaning he's opposed to breastfeeding. Read the tweets, people!
  2. Feminism. I'll be honest, I got lost on this one quite early on. As a disabled woman living in poverty, I count myself as an intersectional feminist. There are various other flavours of feminism. But, y'know, what they all have in common is lots of jargon. If feminism isn't your particular political arena, you're not going to know the buzz words. And Twitter, with its 140 character limit, really isn't the place to explain them, particularly when you're angry. I know, I've got involved in enough arguments on there in my time and just ended up completely frustrated!
One of the worst things I've seen hurled Christian's way is that he hates women because he's gay. Listen to yourselves! How homophobic is that? In my Twitter acquaintance with Christian, he's often replied to his abusers in (rather more polite) kind. Although I've seen him use ableist language thoughtlessly (loons, nutters etc), when I've called him out on it he's always apologised. And I've never seen him use a gendered insult.

He's not perfect, naturally. Which of us is? Retweeting the abuse he receives - or even a simple disagreement - can lead to some of his more devoted fans attacking the original tweeter. That's shit. The fans need more restraint, of course, but when you have quarter of a million followers you have to bear some responsibility for what you tweet.

So, what's the take-home from this post? I think the biggest is that we all have a lot to learn, about our own "home patches" as well as less familiar areas. When someone isn't up to speed on your particular topic, shouting "CHECK YOUR PRIVILEGE" at them really isn't going to help. (Note, I'm not suggesting you shout at Christian. But there are people who do.)

Gender politics is complicated stuff. We're all on a steep learning curve, and we all started somewhere. Don't we owe it to those who are just discovering it to explain things calmly and clearly?

Monday, 24 June 2013

In which I make the mistake of having an opinion about The Voice and disability.

Saturday night saw the final of The Voice on BBC1. Yes, I watch The Voice. Deal with it. It was won by Andrea Begley, who has a severe visual impairment.


But why am I mentioning her disability before her (really rather good) voice, you ask? Well frankly, it was impossible to ignore, the show rammed it down our throats so much.
  • Every video, every link, it was mentioned.
  • I began to think her middle name was Inspirational. Andrea Inspirational Begley. What makes her inspirational over any of the other competitors? Could it be...maybe...nope. No idea. At all. /sarcasm
  • In training videos, Andrea dressed pretty much like the other female competitors: skinny jeans, heels, fitted tops. This makes me suspect that the way she was styled for each show was not her own taste, and was possibly designed to elicit the "ahh" factor. While the other women were in short skirts and tight trousers, Andrea was wearing what I described one week as "my first grown up party dress, aged 12". And always, always the milk-bottle glasses, reminding us of her visual impairment, though I discovered on Google Images while finding pictures for this post that in fact she doesn't always wear them. This chimes with the infantilisation of disabled people, seen as permanently child-like, their every achievement seen as more praiseworthy than that of someone able-bodied.
  • Andrea's coach on the show, Danny O'Donoghue, habitually referred to her as having "the voice of an angel". Andrea's voice is good, but I wouldn't characterise it as particularly angelic. (What does an angel sound like anyway?) Could this be an example of a disabled person being perceived as the eternal innocent? During one of her songs, the tangentially relevant My Immortal, the production even projected a pair of angel wings behind Andrea's shoulders. One (non-disabled) person on my Twitter timeline commented that Andrea was lucky to be blind: she couldn't see them.

So far, so irritating. This was when I made my big mistake. Immediately after the result was announced, I tweeted the following.


Tweeted in anger, I fully admit, and also in pique because my favourite, Leah McFall, hadn't won. But I thought the meaning was clear, specifically the use of the word "if". IF you voted for Andrea because you think she has a wonderful voice, that's cool. But IF you voted for her because she's disabled and brave and inspiring and aww,  then...well, the tweet says it.

Twitter's a funny place, though. If you dare to express an opinion, there are quite a few people who won't actually bother to read it properly, and just attack you instead. I was called quite a variety of things, most of which I wouldn't repeat on here. My block button was red-hot.

But the interesting thing was that several of them said I was the first person to mention that Andrea was blind. Really? Had they been watching the same show I had? Some of what I've mentioned above is fairly subtle, I agree, but the show had been blatant in their mentions of her disability, from her audition on.

As had Andrea herself, in fact. Despite saying she wanted to be judged on her voice rather than her disability, she talked about it in nearly every video. Reality show contestants are always victims to the edit, of course, but editors can only take things out, not add them in.

So what conclusions can I draw from this? I could try not to have so many opinions...but I don't think that's going to happen any day soon. I definitely need not to engage with trolls, just to ignore and block them. I don't need the stress. But you know, isn't it kind of worrying how ingrained disablism is in our society, that people don't even notice something as obvious as this?

PS As I've finished typing this, there's been an interview with Andrea on BBC Breakfast News. First question. "Tell us about your sight?"

Sunday, 19 May 2013

The Impossible Girl (spoilers) #DoctorWho #Spoonie

Last night was the season finale of Doctor Who. I  thought it was one of the best episodes for quite some time, certainly the best of the season. But it also got me to thinking. A major theme was losing and gaining control - both for the Doctor and his current companion, Clara. And that's also a huge issue for spoonies, people with long-term illnesses that cause crippling fatigue.

The baddies in this episode were the Whispermen, who kidnap the Doctor's friends Clara, Vastra, Jenny and Strax to lure him to the one place he must never go: his grave, on the planet Trenzalore.

When we become ill, it's as if we've been kidnapped and taken to a different planet. We are snatched away from our everyday lives, held hostage by the limitations of our conditions.

There is no body in the Doctor's tomb. Instead there is a time tunnel, made of scar tissue from all the Doctor's travels through time and space. The villain of the piece, the Great Intelligence (hammed up wonderfully by Richard E. Grant) enters the time tunnel, aiming to split itself into fragments scattered throughout the Doctor's timeline and corrupt it absolutely, undoing all the good he's done.


Clara follows it into the time tunnel in an attempt to reverse the damage. Things take place around her. Previous incarnations of the Doctor run by. At first she feels out of control. She has no idea what's going on.

Gradually she works out her purpose. The Doctor is always there, though not always in the same form. She can recognise the best thing for the Doctor to do: she saves his life.


It's the same for us. At first, everything is confusion and feeling out of control. Fatigue, pain, brain fog. But gradually, a pattern emerges. We work out what to do. How to live our lives in the best possible way for ourselves and those around us. Maybe we're not saving the Doctor (or maybe you are?) but in our own way we're time lords, pacing and resting so we can do the things we really want to do.

We're the impossible girls and boys. We learn our purpose. We regain control over our lives.

We're spoonies.

Wednesday, 1 May 2013

#BADD Growing Up Beside You

This is Imperial Place, Borehamwood.


A few days ago, someone asked me for directions to get there. I gave the directions. Off he trotted. I assume he got there - I have no reason to think he didn't.

OK, I hear you say. But why am I telling you this little anecdote?

Well, he asked me. There were other people around, but he asked me - the woman in the wheelchair. Unless you use a wheelchair yourself, you have no idea how rare this is.

You're much more likely to find someone looking at you like you're a bit weird because you're laughing, or standing up, or walking a few steps (YOU FRAUD!), or smoking a cigarette, or getting things off the top shelf in the supermarket, or clothes shopping, or drinking alcohol.

I mean, how dare I have anything approaching a normal life? I'm a cripple! It's surprising enough to see me out on my own without a minder, never mind doing things that everyone else - regular people, whose legs and stuff work - does.

Why does this happen? There has been a tradition of "Othering" disabled people, setting up an "us and them" dichotomy. Once disabled people are established as "them", they are seen as one homogenous mass. At the very most, they are split into "wheelchair users", "blind people", "deaf people" and so on. Within each sub-group, there is no scope for variation. So, for instance, a punk rocker using a wheelchair is far more shocking than an able-bodied punk rocker would be.


Other wheelchair users like myself may have experienced the shock it causes when they stand up, or walk a few paces. The standard definition of the subgroup "wheelchair user" is "totally unable to walk", and many members of the general population with no experience of disability are completely thrown by any standing or walking ability.

Similarly, use of a wheelchair is associated in many people's minds with learning difficulties. I have had an assistant in Clinton's Cards telling me how to use a book of stamps. (I told her I was doing a PhD and I thought I would cope.)

What can be done to counter this Othering? More and more exposure to more and more disabled people, showing our variety and the realities of our different lives, and how close they are in so many ways to the lives of everyone else in the world. Yes, that needs a more accessible society and a decent welfare system, so we're maybe talking long-term. But there are some good guys out there already. Think back to my Imperial Place experience.

Each individual like that who "gets it" is one more person who can spread the word that disabled people are - in the end - just people. It's best when it starts in childhood. So what we need to do is for you to grow up beside me, and I'll grow up beside you. Paolo Nutini says it well, I think.


This is my post for Blogging Against Disablism Day 2013. You can find the other links on Goldfish's great blog (which I recommend in general!) here.

Monday, 29 April 2013

Multiple Sclerosis Awareness Week #MSAwarenessWeek

MS Awareness Week starts today, 29th April 2013.

This is the one week a year when we - people with MS, our families and friends, and the organisations that support and inform us -  try to spread the word about what multiple sclerosis is and the many ways, often invisible but nonetheless potentially devastating, it can affect us.


This year's awareness week comes with the disturbing news that only 40% of those eligible to receive one of the seven licensed MS drugs are actually getting them. This may be down to a lack of information and problems accessing specialists. The UK ranks 25th out of 27 in Europe on prescription rates, which given our relative wealth is really not good enough.

Decisions should be taken nationally about this kind of treatment and specialist care plans drawn up for each patient, with regular reviews allowing for treatment options to be assessed on a regular basis.


People with MS tend to do a lot of falling, both physically and mentally. That's OK. The thing is getting up again. Those of you who don't have MS, please understand that this can sometimes take us a little while.

It's MS Awareness Week. But we have to be aware of MS every day of the year.

For more information on MS, please visit:
MS-UK
MS Society
MS Trust

Sunday, 7 April 2013

Placebos, sham surgeries and CCSVI

Recently GPs took part in a survey which showed that 97% of them had used placebos at some point in their careers. The truth is inevitably more nuanced than that headline figure: 97% had used what the researchers called "impure" placebos such as antibiotics for viruses, and the figure for "pure" placebos, treatments containing no active ingredients at all, was in fact 10%.


"Pure", inactive placebos such as sugar pills may seem the more dangerous, but "impure" placebos may be actively dangerous to health. For instance, antibiotics can have side-effects and may promote antibiotic resistance.

Most of the doctors questioned thought that any risk of damaging the trust between doctor and patient was unacceptable, but that it was possible to prescribe a placebo to a patient without actively lying to them. For instance, half of the doctors told the patient that the intervention had helped others.

Is this ethical, particularly if it's possible that the patient would have got better anyway? If something is at the extreme ends of a range of measurements, the likelihood is that it will move towards the average. This is the statistical phenomenon called regression to the mean. The medical application of this is that if someone is ill, on the whole they're likely to get better whether there's any intervention or not.

There may be a psychological effect from receiving a placebo, even if the patient knows that's what it is. One study found that even when the patient was fully aware that their treatment had no active ingredients, the placebo effect was still seen. However there were methodological flaws in that study. More research is needed, to see if the results can be replicated.

Placebos are commonly used in trials to assess whether a new medication is better than no treatment at all. How can a surgical intervention be tested? Sometimes sham surgery is used. Sham surgery forms an important control, as anaesthesia, the incision, post-operative care, and the patient's perception of having had an operation are the same.


However again there are ethical issues, as all surgery has the potential to harm the patient. As a result, sham surgical procedures are rare in human subjects.

In a classic study in 2002, patients with osteoarthritis in the knee either had standard surgery, had their knee joint washed out, or had an incision made in the skin and sewn up again. All the patients in the trial therefore experienced "surgery" of some sort, but didn't know which type. All three groups reported similar levels of pain reduction and improvement in mobility, suggesting that the standard surgery produced no advantage over placebo.

A sham surgery trial has recently reported relating to the controversial CCSVI theory of the causation of MS, which hypothesises that MS is caused by compromised drainage of blood from the central nervous system. The proposed treatment is balloon venoplasty, whereby a small balloon is threaded into the vein and then inflated to clear the blockage. Since 2009, around 30,000 MS patients worldwide have had this treatment, almost always privately rather than as part of a trial.

In this small trial, 30 patients received either the balloon venoplasty treatment or a sham surgery. The treatment did not provide sustained improvement in patients. In fact in some cases, there was a deterioration.

Clearly this was a small study, and more research is needed. But in the meantime, the researchers, who studied under Paolo Zamboni, the developer of the CCSVI theory, have urged patients to enroll for trials rather than pay for the treatment privately.


Overall I believe placebos certainly have a valuable place in research, assuming of course that patients know they may receive the placebo rather than the active treatment. In the GP surgery, I'm not so sure. We should be using evidence-based medicine: that means the best available treatment for the condition, not sugar pills or inappropriate antibiotics. I suspect placebos will always be with us though, one way or the other.

Wednesday, 27 March 2013

Unhelpful response to the #WOWpetition

I don't know if you're already aware of the WOW petition. It was started a little over 3 months ago by comedian Francesca Martinez, and is well on target to achieve 100,000 signatures by its closing date. That means it would considered for debate in the House of Commons.


WOW stands for War on Welfare. Because frankly, that's how it does feel. Like this soulless government has declared war on those of us forced to claim welfare benefits.

Let's say you're on Disability Living Allowance, and when that gets changed over to Personal Indepencence Payment you lose out. Well OK, that's just one thing (apart from the blue badge, and Motability car, and disabled railcard, and so on that it passported it you to). Maybe you can manage without the DLA. Maybe.

But you're also on contributory Employment and Support Allowance, and you've been on it nearly a year. So that's about to stop.

And that's before we get anywhere near the changes to Council Tax Benefit, and to Housing Benefit (the Bedroom Tax).

Tens of thousands of sick disabled people are about to go under financially. And this government just doesn't give a damn. Oh, they always have a soundbite:
There's a lot of misleading stories about the impact of our welfare reforms on disabled people, which could lead to unnecessary scaremongering. Our reforms will make sure the billions we spend every year give more targeted support and better reflect today's understanding of disability. Hundreds of thousands of disabled adults and children will actually receive more support than now with the combined effect of benefit changes under universal credit.
Targeted. Some people receiving more support than now. Well, as someone pointed out to me today (thanks Eggy!) all the NHS funds don't get allocated to intensive care: support is required at all levels of need.

So, returning to the WOW petition, what it asks for (among some other things) is a cumulative impact assessment, not looking at the effect of each benefit "reform" (*spit*) separately, but how people will be affected in real life. Real people are complicated. Lots of us claim more than one benefit (partly because the system's so complex!)

When a government e-petition gets 10,000 signatures, the department responsible for it gives a reply. It's taken a while for the WOW petition's reply to turn up: I only just noticed it, and the petition has over 27,500 signatures.

To summarise the reply, it seems to be:
  • We're not avoiding you.
  • This is hard.
  • The policies haven't all been decided yet.
  • There are impact assessments for individual benefits or for all tax, benefit and expenditure changes across households, but nobody's ever done what you're asking for, which is in between.
  • Did we mention this is hard?
My reply to that would be, with the greatest possible respect (and as civil servants they would know what an insult that is!) pop down to Ryman's, buy a new scientific calculator and get on with it. These are people's lives you're messing around with (at the command of your political masters), and there is a clear case for a cumulative impact assessment to be done.

If you haven't already signed the WOW petition, would you take a look and consider signing it? The more signatures on the petition, the more pressure sympathetic MPs like Michael Meacher can put on the DWP on our behalf.

Thanks!

Edit: I'm all for avoiding unnecessary government expenditure, so I'm sure it would be fine for the DWP to use this cumulative impact assessment, which Scope and Demos have just done. It calculates that those disabled people most severely affected by the cuts will lose £4,600 each year from what are already low incomes. As Richard Hawkes the chief executive of Scope says:
At the moment there’s no place for disabled people in the Chancellor’s aspiration nation.
Sadly, that seems to be very true.

Friday, 22 March 2013

PCC reply to my complaint about Daily Mail cartoon

I complained to the Press Complaints Commission about this cartoon, which was published in the Daily Mail on 25th February 2013.

This is their reply.


Commission’s decision in the case of
Various v Daily Mail

A number of complainants expressed concern regarding a cartoon which had accompanied an article about Disability Living Allowance (DLA). The cartoon had depicted a man with a blister, saying “it’s a bad blister, but a bit of Disability Living Allowance should make it better”.

Complainants considered that the newspaper had breached Clause 1 (Accuracy) by inaccurately suggesting that DLA could be claimed on the basis of such a trivial injury. They also considered that it had been misleading to imply that people in receipt of DLA do not have genuine need for the benefits they receive.

The complainants considered that the cartoon had been discriminatory towards the disabled, in breach of Clause 12 (Discrimination). A number of complainants also said that they had found the article offensive.

The Commission considered the cartoon to have been a satirical commentary on the availability of disability benefits. Cartoons are a well-established method of newspapers making satirical comments about current affairs, and the Commission would be reluctant to compromise the ability of publications to pass commentary in this manner. Nonetheless, regardless of whether the cartoon’s message was satirical, the newspaper was required to observe the terms of the Editors’ Code of Practice. Clause 1 (Accuracy) states that “the press must take care not to publish inaccurate, misleading or distorted information, including pictures” and “the press, whilst free to be partisan, must distinguish clearly between comment, conjecture and fact”.

The Commission was satisfied that readers generally would have recognised that the cartoon expressed the robust, and even controversial, opinion of the newspaper about the general availability of disability benefits, rather than a statement of fact about the precise circumstances in which benefits can be claimed. While the cartoon had suggested that benefits are too readily available, it had not implied that everyone on DLA was receiving it unnecessarily. The newspaper had not failed to distinguish comment from fact. There was no breach of the Code.

Under Clause 12 the press must avoid prejudicial or pejorative reference to an individual’s physical or mental illness or disability and details of an individual’s physical or mental illness or disability must be avoided unless genuinely relevant to the story. The Commission made clear that Clause 12 does not cover references to groups or categories of people. The article had not made discriminatory reference towards an individual. In the absence of reference to a particular individual, the Commission did not establish a breach of Clause 12.

The Commission acknowledged that a number of complainants found the cartoon offensive; however, it made clear that the terms of the Editors’ Code of Practice do not address issues of taste and offence. The Code is designed to address the potentially competing rights of freedom of expression and other rights of individuals, such as privacy. Newspapers and magazines have editorial freedom to publish what they consider to be appropriate provided that the rights of individuals – enshrined in the terms of the Code which specifically defines and protects these rights – are not compromised.  It could not, therefore, comment on this aspect of the complaint further.


I am not satisfied with this response. Does anyone know if there are further steps I can take?

Tuesday, 19 March 2013

Labour doesn't represent me any more

I have voted Labour at every election since I gained my majority, and became a member of the Labour Party around 1990. I am now going to leave the party, and will not be voting for them at future elections. This is not a decision I've reached easily, so I wanted to explain some of my reasons. From conversations with other people, I know I'm not alone.

I have multiple sclerosis and other long-term conditions. I wish I was well enough to work, but I know I'm not. I don't think I'll ever work again, unless there's something I can do from home, for one or two hours each week, and entirely under my own control as and when I feel well enough.


That being the case, I don't think it's extreme to expect society to provide me, and other long-term sick and disabled people, with support. After all, we consider ourselves to be a civilised country, and as Mahatma Ghandi said:
A nation's greatness is measured by how it treats its weakest members.
According to its website, the first and second values on which the Labour Party stands are social justice and strong community & social values. So Labour must agree that sick and disabled people should be supported, right?

Well...it's hard to tell, really. It was the Labour Party which awarded the contract for the unfit for purpose Work Capability Assessments to the iniquitous Atos. They have not, until recently, spoken up against the Welfare Reform Act, which has forced so many genuinely disabled people into abject poverty, and the fear of which has caused many people, sadly, to kill themselves.

Party leader Ed Milliband has relied too much on "I met a man who..." rhetoric, rather than engaging with the issues and meeting those with first-hand knowledge of living with long-term sickness and disability. Was the party trying too hard to keep the support of the middle ground, poisoned as they were by media and ConDem stories of benefit scroungers?

Through all this, and other issues (that's just the one most personal to me), I kept my faith with the Labour Party.

As I write this, the House of Commons is debating emergency legislation brought in by the government so that they don't have to pay back benefit owed to jobseekers after the Poundland workfare ruling. It seems obvious how Labour would vote in this debate. Labour, yes? It's a debate about the use of people's labour. Whether people deserve to be paid for...their labour. The Labour party came out of the whole workers' rights movement. And think back to those values: Social justice. Community and social values.

Well, the Labour Party have told their MPs to abstain.Yep, not vote at all. I mean...what?


So, Labour Party, it's not me, it's you. You walked away from me. You don't represent me any more. I'll be resigning my membership. Ironically, it looks like I'll be abstaining in future elections, as there's no other party I could bring myself to vote for.

And that's the end of me and Labour.

Sunday, 24 February 2013

The #OscarPistorius case: a fallen hero, a horror story, and sick jokes

For as long as I can remember, I've been an athletics fan. It's such a pure form of sport: who can run fastest, jump furthest or highest, throw furthest? It's competitive, but each individual is trying to beat their own personal best mark as well as the competitor in the next lane.

Historically, Paralympic sport has been far less prominent than mainstream, so it's been great to see South African Oscar Pistorius, the "Blade Runner", become one of the best known world sportsmen over the last few years,


Although he was already well known in Paralympic sport, his real fame came after he challenged the IAAF to be allowed to take part in mainstream events. They felt that his artificial legs gave him an advantage over able-bodied runners, claiming he had to use less energy to run with them.

After an appeal, Pistorius was cleared to run with able-bodied athletes, and in 2012 in London he became the first double amputee to compete in an Olympic Games. He also won 2 gold and one silver medal in the 2012 Paralympic Games.

It seemed that Oscar Pistorius was truly the golden boy of the Paralympics movement, and of South Africa. He was a hero to millions around the world (including me) and a role model to disabled young people. What could possibly go wrong?

Early in the morning of 14th February 2013, Oscar Pistorius shot and killed his girlfriend, model and campaigner Reeva Steenkamp. That is not in doubt. The reason for the shooting is: whether it was deliberate or accidental.

I'm not a lawyer, nor was I in the courtroom for the bail hearing, nor obviously in Pistorius's apartment. So I'll confine myself to saying that Reeva Steenkamp's life has been cut tragically short, and her family's lives blighted. And whatever happened, Pistorius will never be the same golden young man again.

Within minutes of news of the shooting appearing on sites like Twitter and Facebook, the jokes started. You would think jokes about a tragic death would be tasteless enough, but these focused on Pistorius's impairment. The same has happened with other disabled personalities, including swimmer Ellie Simmonds after last year's Paralympics.


I'm all for jokes. Humour makes the world go round. But a lot of humour is about power dynamics. As someone put it (sorry, I can't remember who), you can punch up or punch sideways, but punching down just isn't on. As a group, disabled people are less powerful than able-bodied people in society, so by making jokes about their disabilities able-bodied people are punching down.

Disablism isn't always as simple as physical attacks or direct insults against people with disabilities. And being told "Don't be daft, it's just a joke!" or "You just don't have a sense of humour!" doesn't help.

After the UK's excellent performance both in the delivery of the Olympic and Paralympic Games and in competition, it seemed possible that the legacy would include a new attitude to disabled people. On this evidence? Maybe not. We still have a long way to go.

Thursday, 31 January 2013

#Derek: self-indulgence, saccharine and disability

Last night saw the first in Ricky Gervais's new series Derek. I posted about the pilot when it was screened last April, and I've never made any secret of the fact that I wasn't a fan. It seemed unfair for me to dismiss the series without seeing it, though, so I watched last night. The result was many, many thoughts - and here are some of them.


It's in Gervais's customary fly-on-the-wall mockumentary style. 50 year old Derek is a volunteer helper in a care home. His best friends are manager Hannah, odd job man Dougie, and a homeless man, Kev. I couldn't quite work out the purpose of Kev. He is unpleasant, smelly, alcoholic, and sexist, and really just hangs round on the periphery. Perhaps he's meant to be the antithesis of Derek's goodness and innocence?

The first episode had perhaps the most predictable plot possible for a show set in a care home. It was threatened with closure and the characters rallied round to save it. Additionally, of course, this is a timely story, with the current social care cuts.

Channel 4 billed  Derek as as a "bittersweet comedy drama", but to me there was neither enough tension for drama nor enough laughs for a sitcom. I was annoyed by the attempts to signal what emotion we should be feeling:  the sub-Einaudi piano music to show that this was a poignant or sad moment was a prime example. At times I was in danger of dying from a saccharine overdose, such as when Hannah explained the importance of caring.

It has to be said that many people loved the programme. The tweets below are just a couple of many examples.
was an emotional rollercoaster, had me crying & laughing in 30mins. Funny, sad but true and very insightful. (Emma J Fonzarell)
Just caught up with ! Absolutely Fantastic, more comedy brilliance from :) (Lisa Marwick)
But others took issue with the accuracy of the setting:
Have you ever set foot in a care home? I know you think it's hilarious to be misinformed but come on, is lazy writing. (Bitsy)


One issue that keeps coming up is whether the character Derek is disabled. Ricky Gervais continues to insist that he's not, that he's simply naive and innocent, whereas many viewers are in little doubt that Derek has some kind of learning disability. Actor and comedian Peter Serafinowicz questioned:
Why has David Brent got Down's Syndrome? (Peter Serafinowicz)
In  possibly a direct response to criticisms of the pilot, this was raised in the programme, with "man from the council" Roger asking Derek whether he'd ever been tested for autism.
'If I'm autistic would it change me? Would it kill me? Would it make me a different person?' 'No.' 'Then leave it.'
Now that's all fine for Ricky Gervais, but in real life, a diagnosis can be hugely comforting to the parents of a child with autism. A rather glib and uninformed attempt at manipulating the emotions of the viewers.

Derek has been around since the late 1990s. Back in 2001, Ricky Gervais and Stephen Merchant discussed the character. 
"Derek," Ricky begins, "is just a nice, simple lad who sees the world differently." "Yeah," says Steve. "That's the corporate party line. Toeing the party line. The man who sees the world differently. Brilliant."
Hm.

In the end though, does it matter if Derek is disabled or not? A lot of comedy is about people doing stupid things. The problem comes when it goes beyond "mainstream" stupidity. Are we laughing at the characters or with them? In sitcoms like I'm With Stupid disabled characters are played by disabled actors, and the disabled man who originated the idea was story consultant for the series. A character with a disability being played by a non-disabled actor - particularly in a comedy - can raise questions about how accurate and sensitive their portrayal is.

And what effect will the portrayal have on public attitudes to disabled people? Comedian Stewart Lee, writing about the original YouTube videos of the character, said:
"...watching Gervais's Derek Noakes on YouTube, I imagined feral children trailing real Dereks around supermarkets, chanting "Derek Derek", as they doubtless would were the series to be made, and wondered if, sometimes, discretion is not the better part of valour." 
The evidence was on Twitter:
  try an guess who i sm ya fucking beaut!! Bet ya dnt know cause ya (Bernie Wog)
. hey man! Saw ! So glad someone is finally making a sitcom where we can laugh at retards! Classic Mate! (Alex)
And as I recounted in my previous post about Derek, I have had a group of kids shouting "Oi, Derek!" at me in the street.

I suspect what Gervais was aiming for was a version of Forrest Gump, where innocence and goodness triumph in a confusing and wicked world. Did he succeed? Not for me. It was too maudlin. Ricky Gervais can be very funny, but he needs someone - Stephen Merchant does it par excellence - to keep him from tipping over the edge into self-indulgence.

Perhaps if there's another series of Derek, the title character should be played by a disabled actor. I'd take more interest in that.

Thursday, 17 January 2013

Thousands of disabled and sick people will be hit by new ESA/WCA changes #esaSOS

On 28 January 2013 the UK government is due to make a set of changes to the Work Capability Assessment (WCA). The WCA is the flawed ‘fitness to work’ test which assesses whether sick and disabled people can get Employment and Support Allowance (ESA): a benefit designed to help and support very unwell or profoundly disabled people into work.  

Although these changes have been advertised as small ‘amendments’, they will in fact have a huge impact on the way people’s illnesses and disabilities are assessed. Many vulnerable people’s needs will suddenly be able to be overlooked or ignored, meaning they could end up losing the support they desperately need to manage their conditions.

Hundreds of thousands of sick and disabled people across Britain need your help to fight these changes!

PROBLEM 1: FALSE ASSUMPTIONS
In the fitness to work test, your needs are assessed by a ‘healthcare professional’ employed by the French private company ATOS. This assessor doesn’t just need to look at your current difficulties. For example, they can also imagine how using an aid (e.g. a wheelchair) might improve your ability to work and make a judgement based on that – without even asking your opinion!

However, soon this “imaginary test” will be able to be used for many more aids (including guide dogs and false limbs!). This means that soon thousands more people could be judged as fit to work, without being consulted, on the basis of an “imaginary” aid they don’t own or may not be able to use!

It gets worse. Even if returning to work may clearly put you at risk, these changes will mean you can still lose your disability benefit – as long as the assessor believes that trying a new therapy or treatment might reduce that risk. There’s no need for evidence that the treatment will help: you will lose support either way, making it much harder to manage if the treatment doesn’t work as hoped – let alone if it ends up making things worse.

>>> Imagine Bert, who suffers from severe schizophrenia, but is found fit to work and made to take behavioural therapy in the hope of improving his condition. He will lose his disability benefit, without the assessor having to look at several vital questions: how hard it would be for Bert to contact a psychiatrist? How long would an NHS appointment take to organize? Are there private options in his area – and could he afford them if so? What if the therapy doesn’t work, or takes a long time to adjust to? If the government’s rule changes go through, people like Bert who are desperate to work will find it nearly impossible to get an accurate assessment, affecting the quality of their support and actively preventing their efforts to get back into work <<<.  

PROBLEM 2: SEPARATING PHYSICAL AND MENTAL HEALTH
The government is also trying to change the way people’s conditions are assessed by dividing health problems into two separate boxes: ‘physical’ and ‘mental’. So, for instance, when looking at what tasks people can do, only the ‘physical half’ of the test will apply to those with physical disabilities. The same goes for the effects of treatment: for instance., if you’re taking mental health medication, only mental health side-effects will be looked at.

This completely fails to understand the way that many disabilities and illnesses can lead to both physical and mental effects. This is also the case for many common treatments: such as those for schizophrenia, Parkinson’s disease and multiple sclerosis.

>>> Think of Emily, who suffers severe, chronic pain because of nerve damage to her leg. Emily is among the 49% of chronic pain sufferers who also suffer depression as a result of continuous pain. An assessor may see Emily as able to do some work as long as she takes strong painkillers for the rest of her life, meaning she could pass the ‘fitness’ test. Yet the painkillers may not deal with the depression caused by her condition. Painkillers have also often been shown to affect people’s wakefulness and decision-making. So taking the medication may affect Emily’s ability to do a job in a completely new way – yet because these new problems are cognitive, they would not need to be looked at by the assessor when making their decision. <<<

Pretending the effects of illnesses and disabilities can be separated in this way goes against all medical practice. Going even further, and using this method to ignore sick and disabled people’s needs, is at best hopeless policy, and at worst deliberate cruelty. We cannot let the government treat some of the most vulnerable people in British society in this way.  

HOW YOU CAN HELP
The main way you can help is by spreading the message about these changes to ESA. The government have tried to sneak them under the radar – the last thing they will want is people talking about them! 
1) Email your MP (you can search by name or constituency at http://www.parliament.uk/mps-lords-and-offices/mps/);
2) Share this blog post on twitter (using the hashtag #esaSOS), Facebook and other social media. Click on the buttons below this post to share on Twitter and Facebook.
3) Email your friends and family a link to this post – or simply talk to them about it! Again, the main way we can get the government to reconsider is by getting people to talk about the injustice of these changes.So please spread the word as far and wide as you can!

Thank you so much for reading this far. Now let’s make sure these unwanted, damaging benefit changes never see the light of day!  

If you want to do more, please sign #WOWpetition and call on the government to think again.  Ask all of your friends to sign too!

The full #Spartacus briefing on the proposed changes to ESA can be found here.